Talking Science Podcast
Anaesthesia – Switching Consciousness Off and On
Ask anyone who has had a general anaesthetic what going under felt like, and most will say it did not feel like anything. They were counting backwards from ten, and then a nurse was asking how they felt. Somewhere around seven, the intervening hours simply vanished, with no dreams and no sense of time passing.
That missing stretch is one of the most remarkable things modern medicine does. Every day in operating theatres across Australia, people are deliberately switched off, their pain, memory and movement suspended long enough for a surgeon to work, and then switched safely back on. Stranger still, after nearly two centuries, nobody can fully explain how it happens.
Surgery Before the Switch
Before anaesthesia, surgeons were judged by the speed of their hands. Patients were awake for every cut, held down by assistants, with perhaps a swig of alcohol or a leather strap to bite. Many chose to live with a dangerous condition rather than face the knife.
Around 1800 the chemist Humphry Davy noticed that nitrous oxide, now known as laughing gas, dulled pain, but for years it was treated mostly as a party novelty. The turning point came in October 1846 in a Boston operating theatre now nicknamed the Ether Dome, where a dentist named William Morton gave a patient ether vapour before a surgeon removed a tumour from his neck. The patient felt nothing, and the news spread around the world within months. Soon after, the Scottish obstetrician James Simpson introduced chloroform, which got an enormous public boost when Queen Victoria accepted it during the birth of one of her children.
Three Kinds of Without Sensation
The word anaesthesia comes from Greek roots meaning without sensation, but it is really a family of techniques.
- Local anaesthesia numbs one small patch, like a tooth at the dentist, while you stay fully awake.
- Regional anaesthesia numbs a whole region, such as a limb or everything below the waist, by targeting the nerves that serve it. An epidural during childbirth is a familiar example.
- General anaesthesia reversibly switches off consciousness itself.
The first two are well understood. A nerve fires by rapidly shifting the electrical charge across its membrane, letting sodium and potassium rush through tiny gateways called ion channels. That shift, an action potential, sweeps along the nerve like a wave. Our article on the nervous system explains this wiring in more depth. Local anaesthetics such as lidocaine block the sodium channels, so the signal cannot form and nothing from that nerve reaches the brain, however much damage is happening. It is like unplugging one line from a switchboard while everything else keeps working.
A Recipe, Not a Single Drug
General anaesthesia aims for several effects at once: unconsciousness; amnesia, so no memories form, which is subtly different; analgesia, blunting the body's stress response to injury; and often muscle relaxation, keeping the body still. No single drug does all of that well, so anaesthetists combine several at lower individual doses, an approach called balanced anaesthesia that tends to mean fewer side effects.
Induction, putting someone under, is commonly done with an intravenous drug such as propofol, a milky-white liquid that brings unconsciousness within seconds, which is why people drift off mid-countdown. Maintenance keeps them there with a continuous infusion or a controlled concentration of anaesthetic gas, adjusted throughout. At the end the drugs are stopped, and because modern agents are cleared quickly, broken down by the liver or simply breathed out, consciousness returns within minutes. Some grogginess afterwards is entirely normal.
The Honest Gap in Our Knowledge
Anaesthetic drugs are among the most widely used medicines in the world, and their safety is backed by immense experience. Yet there is still no complete, agreed explanation of exactly how they produce unconsciousness.
There are strong clues. More than a century ago, researchers noticed that the potency of very different anaesthetic gases tracks closely with how readily each dissolves in fats and oils. This pattern, the Meyer-Overton correlation, suggested anaesthetics might work by slipping into the fatty membranes around nerve cells, and the idea dominated much of the twentieth century. More recent research points to specific receptors instead. Many anaesthetics boost a receptor called GABA-A, which responds to the brain's main calming messenger, effectively turning up the brain's own brakes until consciousness cannot be sustained. Others act on receptors for glutamate, an excitatory messenger, so there may be several partly overlapping routes to the same outcome. The deepest uncertainty lies in linking these cellular effects to the far bigger question of what unconsciousness actually is across the whole brain.
Watching Over a Sleeping Brain
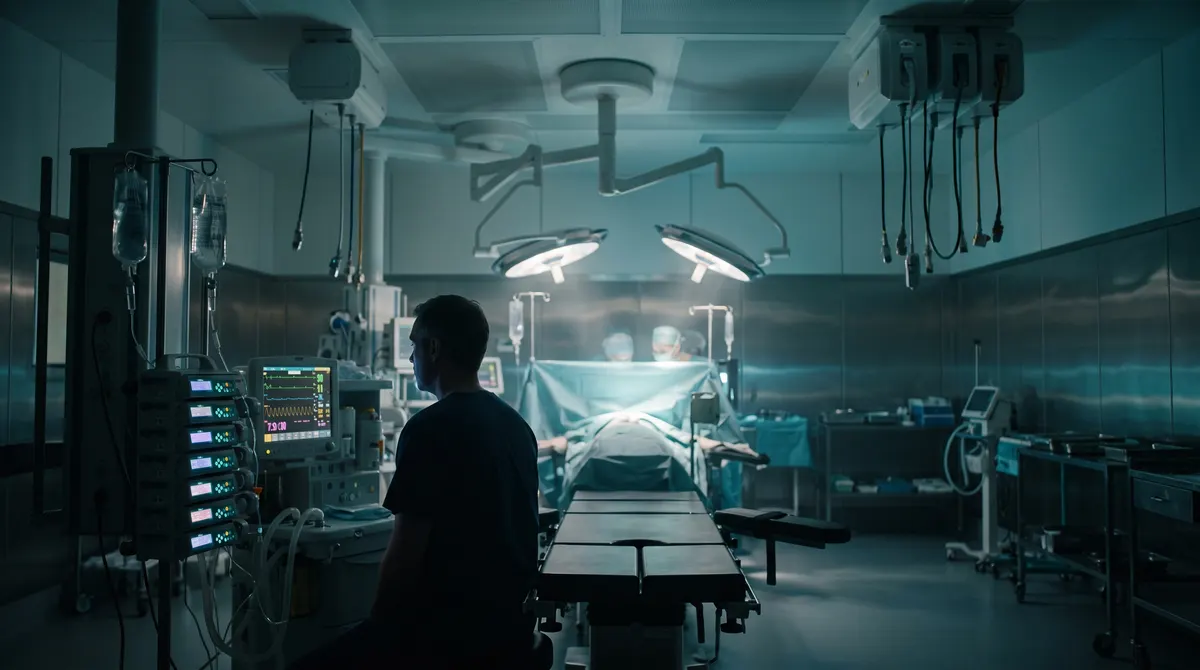
Not knowing exactly how something works is different from not knowing whether it works safely. Anaesthetists watch heart rate, blood pressure and breathing continuously. A fingertip pulse oximeter shines light through the skin to estimate blood oxygen, and capnography measures carbon dioxide in every exhaled breath. Increasingly, scalp electrodes feed brainwave monitors that boil complex activity down to a single number estimating depth of anaesthesia, read alongside clinical judgement rather than replacing it.
That vigilance matters because of intraoperative awareness, a rare event where a patient becomes partly conscious during surgery. Estimates vary considerably with how studies look for it; some suggest awareness with later recall in the order of one or two cases per thousand general anaesthetics, while large surveys based on patients reporting it themselves find it far less often. It is more likely in emergency surgery, some heart and obstetric procedures where lighter anaesthesia is used for safety, and in people who clear the drugs unusually quickly, and monitoring and dosing practices have been refined with this risk in mind.
What It Made Possible
Anaesthesia did not just make surgery kinder. When speed was everything, surgeons were limited to quick, external procedures. Once a patient could be kept still, unconscious and pain-free for hours, operations on the heart, the brain and the abdomen became possible. Risk rises with age, heart or lung disease and the length or urgency of an operation, which is why a pre-operative assessment matters and why the choice between local, regional and general anaesthesia is made patient by patient. In Australia, specialist anaesthetists complete years of training after their medical degree, overseen by the Australian and New Zealand College of Anaesthetists.
A Mystery We Use Every Day
The next time someone you love counts backwards and drifts off around seven, remember what is happening. A carefully chosen mix of drugs is switching off not just pain but awareness itself, reliably and reversibly, by a mechanism science has not finished mapping, while a specialist watches every breath. Enormous benefit and complete understanding do not always arrive together, and anaesthesia is one of the clearest proofs of that.